Medical disclaimer: This article is for general information only. It is not medical advice, and it does not replace advice from a licensed healthcare professional. Prescription medicines for depression require a valid prescription after a consultation with a qualified prescriber. Never start, change, or stop a prescription medicine on the basis of an article alone.
When people search for the best depression medications, they usually want a simple answer: one medicine that works for everyone. In real life, there is no single winner. Depression is not one condition with one cause, and people respond differently to the same medicine. What works well for one person may cause troublesome side effects for another, or may not help enough at all.
This plain-language guide explains the main classes of antidepressants, how prescribers usually choose between them, how long they take to work, and the safety questions worth asking at a first appointment. It will not tell you which medicine to take. Only a licensed prescriber who knows your history, other conditions, and other medicines can do that.
There Is No Single “Best” Antidepressant — Why Fit Matters
Most guidelines describe several antidepressants as similarly effective on average for moderate to severe depression. The differences that matter most in practice are side effects, how a medicine fits with your other health problems, how it interacts with medicines you already take, and whether you can take it regularly and safely.
A prescriber will usually consider your main symptoms first. Is low mood the main problem, or is anxiety, poor sleep, low energy, or chronic pain just as prominent? They will also ask about past responses to medicines, family history, pregnancy plans, liver or kidney problems, heart conditions, seizure history, and substance use. All of these can narrow the choice.
Cost, availability, and how often a medicine needs to be taken also matter. A medicine that is hard to obtain or hard to remember is less likely to help, however good it looks on paper. That is why the first prescription is often a starting point, not a final decision. Follow-up appointments in the first weeks are part of the treatment, not an extra.
Talking therapy is also an important part of care for many people. Guidelines commonly recommend psychological therapy alongside medicine, or on its own for milder depression. Medicine is one tool, not the whole treatment plan.
The Main Classes at a Glance
Antidepressants are grouped by how they affect chemical messengers in the brain, mainly serotonin, norepinephrine (also called noradrenaline), and dopamine. The table below gives a plain-language overview. It is a summary for learning, not a ranking.
| Class | Examples | How prescribers often think about it |
|---|---|---|
| SSRIs (selective serotonin reuptake inhibitors) | Sertraline, escitalopram, fluoxetine, paroxetine, citalopram | Usually first-line for many adults. Generally well studied, with a familiar side-effect pattern. |
| SNRIs (serotonin-norepinephrine reuptake inhibitors) | Venlafaxine, duloxetine, desvenlafaxine | Sometimes chosen when pain or low energy is prominent, or when an SSRI has not helped enough. |
| Atypical antidepressants | Bupropion, mirtazapine, vortioxetine | Chosen for particular symptom patterns, for example when sleep, appetite, or sexual side effects are a concern. Each works differently from the others. |
| Older antidepressants: TCAs and MAOIs | Amitriptyline, nortriptyline, phenelzine, tranylcypromine | Used less often today. They can help some people, but they usually need closer monitoring and have more interactions and dietary or safety cautions. |
| Newer and specialist options | Esketamine, and augmentation with other medicines | Specialist only, usually for depression that has not responded to several standard treatments. These need specialist assessment and monitoring. |
Within the atypical group, bupropion is sometimes discussed when low energy and concentration are prominent, and when sexual side effects are a concern. A comparison with a stimulant used for ADHD is not the same as a comparison with another antidepressant, so it is worth reading carefully: see our guide to Bupropion vs Adderall. Mirtazapine is sometimes considered when poor sleep and poor appetite are major problems, because it can be sedating and can increase appetite. Vortioxetine is a newer option that some prescribers consider when thinking and concentration problems are prominent.
How Long Do Antidepressants Take to Work?
Antidepressants do not work like painkillers. Most people do not feel the full benefit in the first few days. Some early changes, such as slightly better sleep or less anxiety, may appear in the first one to two weeks. Mood, energy, and interest in everyday activities usually improve more slowly, often over four to six weeks.
Prescribers usually review progress after a few weeks and may adjust the plan if there is no improvement at all after six to eight weeks at a suitable level. That review is not a failure. It is how treatment is meant to work: start, monitor, and adjust.
Taking the medicine every day, as prescribed, matters more than most people expect. Missing doses can make it harder to judge whether a medicine is helping, and it can increase the chance of unpleasant effects when restarting. If you miss doses often, tell your prescriber rather than hiding it. They can help with practical solutions, such as a reminder routine or a different schedule.
It is also worth keeping simple notes in the first weeks: sleep, appetite, energy, mood, and any side effects. A short note is easier to discuss at a follow-up appointment than trying to remember how the last month felt.
Common Side Effects by Class — and What to Discuss Early
All medicines can cause side effects, and antidepressants are no exception. Many early side effects are mild and improve as the body adjusts over the first one to two weeks. Others may persist, and they are a common reason people stop treatment. Talking about them early usually leads to a better plan than stopping quietly.
- SSRIs and SNRIs: nausea, headache, sleep changes, restlessness, sweating, and sexual side effects are among the most commonly reported. SNRIs may also raise blood pressure in some people, so blood pressure checks matter.
- Bupropion: can cause dry mouth, insomnia, and appetite changes. It is not usually the first choice for people with a seizure history, and a prescriber will screen for that.
- Mirtazapine: often causes drowsiness and increased appetite, which some people welcome and others do not.
- TCAs: can cause dry mouth, constipation, blurred vision, drowsiness, and changes in heart rhythm, which is one reason they are used more selectively today.
- MAOIs: have important interactions with certain foods and with many other medicines, so they need careful guidance and a full medicine review.
Serious side effects are less common, but they are the reason follow-up matters. Tell a prescriber promptly about severe agitation, unusual restlessness, confusion, a rash, swelling, severe headache, or thoughts of harming yourself. Also tell them about any new medicine, supplement, or herbal product you start, because interactions are common and sometimes serious. This is especially important with painkillers, migraine medicines, and herbal products such as St. John’s wort.
Safety First: The Boxed Warning and When to Seek Urgent Help
Antidepressants carry a boxed warning, the strongest warning the U.S. Food and Drug Administration (FDA) places on a medicine label. It warns that antidepressants may increase the risk of suicidal thinking and behavior in children, adolescents, and young adults. The warning does not mean the medicine should never be used in these age groups. It means that close monitoring is essential, especially during the first few weeks and after any change in treatment.
Anyone starting an antidepressant, and the people close to them, should watch for new or worsening depression, unusual changes in mood or behavior, agitation, restlessness, panic, irritability, or thoughts of self-harm. If any of these appear, contact a prescriber or a mental health professional promptly, and do not wait for the next routine appointment.
Seek urgent help right away if you feel you may act on thoughts of harming yourself, or if someone close to you is in immediate danger. In the United States, you can call or text 988 to reach the Suicide and Crisis Lifeline, or call emergency services on 911. If you are outside the United States, use your local emergency number or crisis service. Staying with a trusted person until help arrives can also make a real difference.
Other safety points deserve the same attention. Tell your prescriber about pregnancy, breastfeeding, or plans to become pregnant, because the balance of benefits and risks is individual. Also mention alcohol use, because alcohol can worsen depression and increase drowsiness with some medicines. Finally, store medicines safely and out of reach of children, and never share a prescription medicine with another person.
Depression With Anxiety, Pain, Insomnia or ADHD — How That Changes the Choice
Depression rarely arrives alone. When anxiety is also present, prescribers often favor medicines that help both mood and anxiety, and they monitor restlessness closely in the first weeks.
When chronic pain is part of the picture, an SNRI such as duloxetine is sometimes considered, because it is also used for some pain conditions. When sleep is the main problem, the prescriber may look at the whole pattern first: a sedating antidepressant, a separate sleep plan, or a short-term sleep medicine may be discussed. Trazodone is one medicine sometimes prescribed for sleep, and like all prescription medicines it requires a valid prescription after consultation.
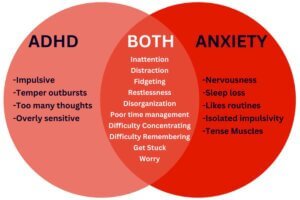
When ADHD is present as well, the picture is more complex, because some antidepressants and ADHD medicines affect attention and energy in different ways. Read our guides to Zoloft (sertraline) and ADHD and to ADHD and depression for background, and discuss any combination only with your prescriber.
Questions to Ask Your Prescriber at a First Appointment
- Which medicine are you considering, and why this one for me?
- What side effects should I watch for in the first weeks?
- How long before we review whether it is helping?
- What should I do if I miss a dose?
- Which other medicines, supplements, or alcohol should I avoid?
- How do I contact you if I feel worse?

What Happens If the First Medication Does Not Help?
If the first medicine does not help enough after several weeks, prescribers usually review the plan. Options include switching to a different class, adding another medicine, or adding talking therapy. A medicine that did not help still guides the next choice.

Stopping Antidepressants: Why Tapering Needs Medical Guidance
Do not stop suddenly. Stopping abruptly can cause flu-like symptoms, dizziness, vivid dreams, and a return of depression. If you wish to stop, ask your prescriber for a tapering plan and a follow-up appointment.
Frequently Asked Questions
What is the best medication for depression? There is no single best one. The choice depends on your symptoms, other health conditions, side effects, and past response.
How long do antidepressants take to work? Some early changes appear in one to two weeks. Full benefit often takes four to six weeks.
What are the side effects of antidepressants? Nausea, sleep changes, and sexual side effects are common. Many early effects ease with time, but tell your prescriber about anything persistent.
What is the first-line treatment for depression? SSRIs are usually first-line for many adults, when suitable. Talking therapy is often recommended alongside medicine.
Can depression medication be stopped suddenly? No. Stopping suddenly can cause withdrawal symptoms and a return of depression. Taper only with medical guidance.
Sources and Further Reading
Sources: National Institute of Mental Health — Depression; MedlinePlus — Depression; NHS — Antidepressants; NICE Guideline NG222 — Depression in adults.
Medical disclaimer: This article is for general information only and is not medical advice. Always consult a licensed healthcare professional before starting or changing treatment. Prescription medicines require a valid prescription after consultation. You can browse prescription medicines at SafeHealth247, where a valid prescription is required.